Subtotal $0.00

Feel Free To Contact Us at
- Phone:(888)-896-5577
- Email:dr.koffler@hmwcenter.com

Subscribe to our Newsletter and get the latest updates in the field of Holistic Medicine
Pentadeca Arginate (PDA) and BPC-157 are closely related. Pentadeca Arginate is generally described as an arginate salt form of the same 15-amino-acid BPC-157 peptide sequence. Most published research, however, focuses on BPC-157 rather than PDA specifically.
Preclinical studies of BPC-157 have investigated tissue repair, blood-vessel formation, inflammation, gastrointestinal biology, and musculoskeletal recovery. However, human evidence remains limited, and there are no high-quality clinical trials establishing that PDA is safer, more effective, or better absorbed than BPC-157.
Feature | Pentadeca Arginate (PDA) | BPC-157 |
Peptide sequence | Same BPC-157 sequence | GEPPPGKPADDAGLV |
Main difference | Arginate salt/formulation | Parent peptide/formulations |
Research base | Very limited | Larger preclinical literature |
Human evidence | Not established | Limited |
Proven injury treatment | No | No |
FDA-approved treatment | No | No |
Proven superiority | No | No |
The key point is simple: BPC-157 has more research, but that does not mean it has been clinically proven to work. PDA has even less direct evidence.

BPC-157, or Body Protection Compound-157, is a synthetic 15-amino-acid peptide.
Research has investigated BPC-157 for potential effects on:
Much of this evidence comes from animal and laboratory studies, rather than large human clinical trials. That distinction matters. Promising biological activity in animals does not establish that a peptide is an effective or safe human treatment.

Pentadeca Arginate, commonly called PDA, is generally described as an arginate salt form of BPC-157.
The “Pentadeca” terminology refers to the 15-amino-acid peptide, while “Arginate” refers to the formulation involving arginine as the counter-ion. The important takeaway is that PDA is not simply a completely different “healing peptide.” The distinction primarily concerns formulation.
A change in salt form can potentially affect properties such as:
But a formulation change does not automatically prove greater clinical effectiveness.
This is one of the most common claims surrounding Pentadeca Arginate.
You may see claims that PDA:
These claims need to be separated carefully.
Greater chemical stability does not automatically mean greater human bioavailability.
To establish superior oral absorption, researchers would need human pharmacokinetic studies measuring how much intact peptide reaches circulation, how quickly it appears, how long it remains, how it is metabolized, and where it distributes.
Those comparative human data are not established for PDA.
There is currently no reliable clinical evidence demonstrating that PDA is better than BPC-157.
There are no high-quality randomized trials showing PDA is superior for:
The comparison is therefore primarily a formulation question, rather than a proven clinical winner-versus-loser comparison.
This is one of the biggest sources of confusion online.
A common chain of reasoning looks like this:
BPC-157 animal study → PDA contains the BPC-157 sequence → therefore PDA produces the same clinical result.
That conclusion is not automatically valid.
Changing a formulation can potentially affect:
Therefore, research conducted with one BPC-157 formulation should not automatically be presented as direct evidence for another formulation.
BPC-157 has generated interest because laboratory and animal research has investigated several processes involved in tissue repair.
Angiogenesis is the formation of new blood vessels. New vessels can help injured tissue receive oxygen and nutrients during repair.
This is one of the most popular claims surrounding BPC-157.
Animal studies have reported findings involving tendon, ligament, muscle, and connective-tissue injury. However, human tendon injuries are influenced by factors such as:
Therefore, preclinical evidence does not establish BPC-157 as a proven tendon-healing treatment in humans. There is even less evidence demonstrating that PDA produces better tendon outcomes than BPC-157.
BPC-157 has been studied in animal models involving muscle and connective-tissue injury, which has contributed to its popularity among athletes and physically active adults.
But “recovery” can mean many different things, including:
These are different clinical outcomes and require appropriate human studies. The same limitation applies to claims surrounding joint pain, arthritis, cartilage injury, and tendonitis.
BPC-157 has substantial preclinical gastrointestinal research, including studies involving ulcers, intestinal injury, inflammation, and gastrointestinal protection.
However, these findings should not be confused with proof that BPC-157 treats human gastrointestinal disease.
The original evidence review also highlights FDA’s 2026 consideration of BPC-157-related bulk substances for ulcerative colitis, where concerns included insufficient evidence of effectiveness and safety.
No.
BPC-157 is not an FDA-approved treatment for tendon injuries, ligament injuries, muscle injuries, wound healing, arthritis, ulcerative colitis, Crohn’s disease, or general recovery.
Likewise, no FDA-approved clinical indication for Pentadeca Arginate has been established. FDA advisory or compounding-related discussions should also not be confused with FDA drug approval.
There is not enough human evidence to establish that PDA has fewer side effects or is safer.
Claims that PDA is:
would require direct comparative clinical studies. A different salt form may change pharmaceutical properties, but that does not automatically establish a different clinical safety profile.
Because human research remains limited, the complete safety profile of BPC-157 is also not well characterized.
Potential concerns with experimental peptide products can include:
FDA has also identified concerns involving characterization and potential immunogenicity for certain BPC-157-related compounded substances.
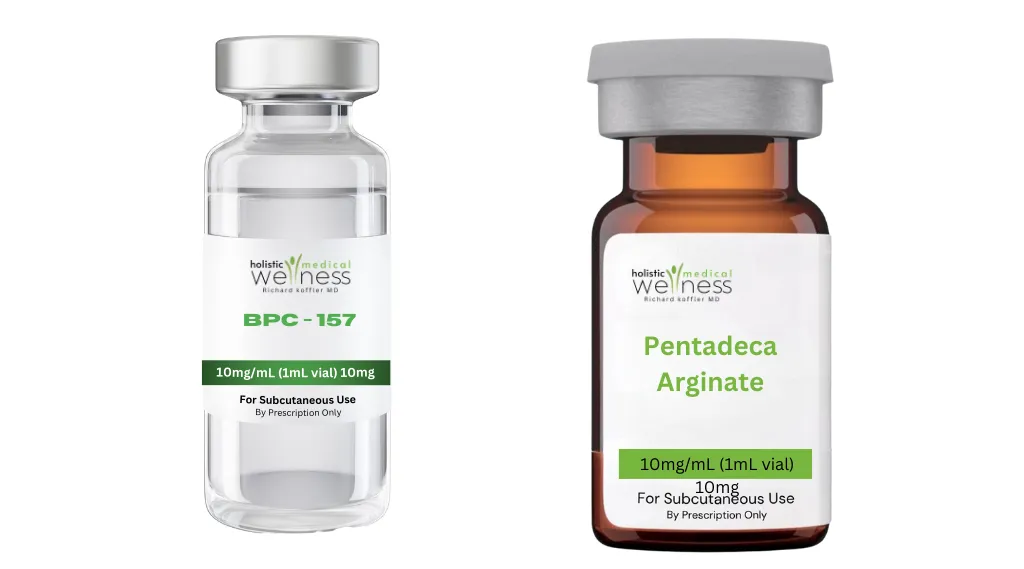
BPC-157 clearly has the larger research base.
But this should not be interpreted as “BPC-157 is clinically proven.”
Evidence category | BPC-157 | Pentadeca Arginate |
Preclinical research | More extensive | Much more limited |
Human research | Limited | Insufficient |
Large randomized trials | Not established | Not established |
Validated dosing | Not established | Not established |
Long-term safety | Unknown | Unknown |
Proven superiority | No | No |
BPC-157 has more research; PDA has less direct evidence; neither has the clinical evidence base of an established approved treatment.
There is no established evidence showing that combining PDA and BPC-157 provides additional benefit.
Because PDA is generally described as a formulation of the same peptide sequence, taking both does not automatically create two independent biological mechanisms.
More exposure also does not necessarily mean more healing. Without validated human dose-ranging studies, online dosing protocols should not be treated as established medical standards.
Pentadeca Arginate and BPC-157 are closely related, with PDA generally described as an arginate salt form of the BPC-157 peptide sequence.
BPC-157 has considerably more preclinical research involving tissue repair, gastrointestinal biology, inflammation, and musculoskeletal injuries. However, human evidence remains limited, and this research does not establish BPC-157 as a proven treatment.
PDA has an even smaller direct evidence base. Claims that its arginate formulation makes it more stable, better absorbed, safer, or more effective require direct comparative research.
So, which is better?
At present, there is no reliable clinical evidence establishing PDA as superior to BPC-157 or either as a proven treatment for injury recovery or other commonly marketed uses.
They are closely related. Pentadeca Arginate is generally described as an arginate salt form of the same 15-amino-acid BPC-157 peptide sequence.
There is insufficient clinical evidence to establish that PDA is better, safer, or more effective than BPC-157.
PDA is marketed around potential formulation and stability advantages, particularly in acidic environments. However, greater chemical stability does not automatically prove better human absorption or clinical outcomes.
There is no established body of high-quality human clinical research demonstrating PDA's effectiveness or long-term safety.
Yes, but human research remains very limited compared with the much larger preclinical literature.
Animal research is promising, but large controlled human trials have not established BPC-157 as a proven tendon-healing treatment.
No. BPC-157 is not an FDA-approved treatment for tendon injuries, gastrointestinal disease, muscle injuries, or general recovery.
No FDA-approved clinical indication for Pentadeca Arginate has been established.
That has not been established through adequate human pharmacokinetic studies. Claims of improved oral bioavailability remain unconfirmed clinically.
BPC-157 has considerably more research, but that does not mean it is clinically proven. PDA has less direct evidence, and there is no reliable evidence establishing either as superior.

It is crucial to discuss peptides like Pentadeca Arginate and BPC-157 with a knowledgeable medical provider because their effects, dosages, and potential interactions with other treatments vary significantly from person to person. A healthcare professional who understands peptide therapy can help assess your individual needs, medical history, and any underlying conditions to ensure the safe and effective use of these compounds. Additionally, while peptides show promising benefits in areas like muscle recovery, inflammation reduction, and gut healing, the research—particularly in human trials—is still emerging, making expert guidance essential to avoid unwanted side effects or ineffective use. Consulting with a trained provider can help you make informed decisions, optimize treatment outcomes, and ensure that peptide therapy is safe for your health.
By sharing this article, you might help a friend, family member, or fellow athlete discover the healing power of peptides. Whether it’s for recovery, reducing inflammation, or improving gut health, the right peptide could be the solution they’ve been searching for.
Ready to take your recovery to the next level? Drop a comment below or share this post with someone who needs to know about these cutting-edge treatments. Let’s start a conversation!






